Introduction
Pain on the very top of the shoulder — the kind you can often point to with one finger — frequently comes from the acromioclavicular joint, usually shortened to the AC joint.
This small joint sits where the collarbone meets the highest point of the shoulder blade. It handles a surprising amount of load, and it is one of the most commonly injured and most commonly arthritic joints in the shoulder. AC joint problems tend to show up during reaching across the body, lifting overhead, bench pressing, and lying on the affected side at night.
Acromioclavicular joint pain is easy to confuse with other shoulder problems, particularly rotator cuff injuries, which cause pain in a different location and respond to different treatment. Getting the source right is the first step toward the right treatment.
This guide covers how the AC joint is built, what causes pain there — from arthritis to injury to a condition common in weightlifters — how it is diagnosed, and the full range of treatment options from rest and physical therapy to surgery.
Anatomy of the AC Joint
Where it is
The AC joint sits on top of the shoulder, at the outer end of the collarbone. You can usually feel it as a small bump or ridge by tracing your collarbone outward until it meets the shoulder.
The two bones
- The clavicle — the collarbone, running from the breastbone out to the shoulder
- The acromion — a bony projection at the top of the shoulder blade (scapula)
The current article describes the acromion as another name for the shoulder blade. It is not. The acromion is one part of the shoulder blade — the flat, bony shelf that forms the highest point of the shoulder.
What holds it together
The AC joint is stabilized by two sets of ligaments, and the distinction between them matters for understanding injury grades:
- The acromioclavicular ligaments wrap around the joint itself and provide horizontal stability — they stop the collarbone sliding forward and backward.
- The coracoclavicular ligaments run from the underside of the collarbone down to the coracoid process, another projection of the shoulder blade. They provide vertical stability and are the main structures preventing the collarbone from riding upward.
Between the bone ends sits a small disc of cartilage, which begins to degenerate from a surprisingly young age in most people.
What it does
The AC joint allows small gliding and rotational movements between the collarbone and shoulder blade. These movements are small but essential: they let the shoulder blade move smoothly as the arm is raised, particularly overhead. Because the AC joint transmits force between the arm and the rest of the skeleton, it takes significant load during lifting, pushing, and falls, which is why acromioclavicular joint pain so often develops in people who lift, push, or play contact sports.
What Causes Acromioclavicular Joint Pain?
Osteoarthritis
The most common cause of ongoing AC joint pain, particularly after middle age.
The cartilage in the AC joint begins to degenerate early, and arthritic changes on imaging are very common in people over 40 — many of whom have no symptoms at all. When symptoms do develop, the joint becomes painful with use, bone spurs may form, and the joint can become visibly enlarged.
Risk rises with:
- Age
- Heavy manual work
- Weightlifting, particularly bench press, dips, and overhead pressing
- A previous AC joint injury, which substantially raises the risk of arthritis developing years later
Acute injury — AC joint separation
A fall directly onto the point of the shoulder, typically with the arm tucked at the side, drives the shoulder blade downward while the collarbone stays in place. This tears the ligaments holding the joint together. It is common in cycling, skiing, rugby, football, and hockey.
This injury is often called a separated shoulder — which is different from a dislocated shoulder, where the ball of the upper arm comes out of its socket. The current article conflates the two. Injury severity is graded, covered in the next section.
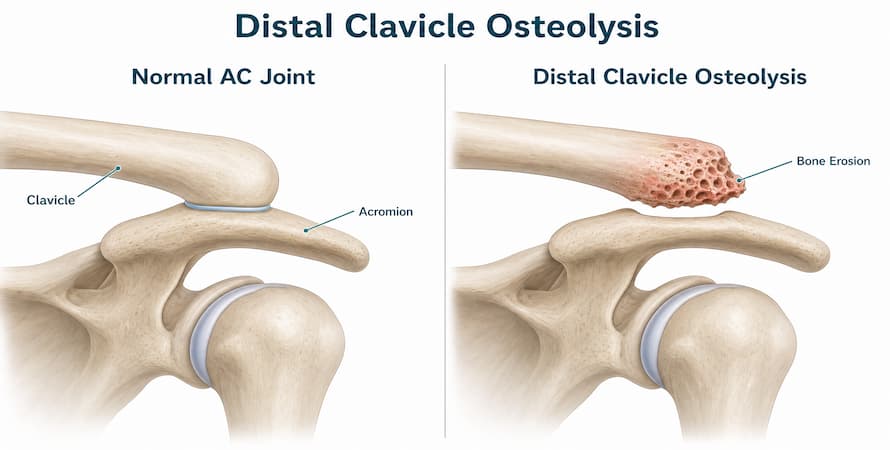
Distal clavicle osteolysis
A condition in which the outer end of the collarbone gradually breaks down, strongly associated with repetitive heavy lifting. Covered in Section 5.
Other contributing factors
- Repetitive overhead activity — painting, construction, overhead sports
- Inflammatory arthritis such as rheumatoid arthritis, which can affect the AC joint alongside other joints
- Infection — rare, but important to consider if the joint is hot, red, and associated with fever
A correction to the current causes list
The existing article lists frozen shoulder and rotator cuff tears as causes of AC joint pain. They are not. They are separate shoulder conditions that affect different structures. They can occur alongside AC joint problems, and AC joint bone spurs can contribute to rotator cuff irritation, but they do not cause AC joint pain.
AC Joint Separation: The Injury Grades
AC joint injuries are graded from I to VI using a system known as the Rockwood classification. The grade depends on which ligaments are torn and how far the collarbone has moved, and it largely determines treatment.
| Grade | What is injured | What it looks like | Usual treatment |
|---|---|---|---|
| I | AC ligaments sprained; no tear | No deformity, tender over the joint | Non-surgical |
| II | AC ligaments torn; CC ligaments sprained | Slight bump; mild displacement | Non-surgical |
| III | AC and CC ligaments torn | Obvious bump; collarbone displaced upward | Usually non-surgical first; surgery debated |
| IV | AC and CC ligaments torn | Collarbone pushed backward into the muscle behind | Surgical |
| V | Severe tearing including overlying muscle attachments | Marked upward displacement; very prominent bump | Surgical |
| VI | Complete tearing | Collarbone driven downward beneath bone — rare | Surgical |
What this means in practice
Grades I and II make up the majority of AC injuries and usually recover well with rest, a sling for comfort, and rehabilitation.
Grade III is the grade where treatment decisions genuinely vary. Most people are treated non-surgically first and do well. Surgery may be considered for people who remain symptomatic after rehabilitation, heavy manual workers, and overhead athletes such as throwers.
Grades IV, V, and VI are generally treated surgically, because the degree of displacement is unlikely to recover adequately on its own.
The visible bump
A bump on top of the shoulder after an AC injury is often permanent, even in injuries that heal well functionally. It is a cosmetic change rather than necessarily a sign of ongoing problems, and many people with a visible bump have full function and no pain.
Distal Clavicle Osteolysis
What it is
Osteolysis means bone breakdown. In distal clavicle osteolysis, the outer end of the collarbone — the part that forms the AC joint — gradually loses bone density and begins to erode.
It is sometimes called weightlifter’s shoulder, because it is most strongly associated with repetitive heavy lifting.
Who gets it
- Weightlifters and bodybuilders, particularly those doing heavy bench press, dips, and push-ups
- Manual workers whose jobs involve repeated heavy lifting or pushing
- Athletes in throwing and contact sports
It can also follow a single injury to the joint, though the repetitive-stress form is more common.
How it presents
- Aching pain on top of the shoulder, at the AC joint
- Pain during and after bench press and similar pushing movements
- Tenderness over the outer end of the collarbone
- Pain with reaching across the body
- Usually no memorable injury — it develops gradually
How it is diagnosed
X-rays may show loss of bone density, irregularity, or widening at the outer end of the collarbone. MRI is more sensitive and shows swelling in the bone before X-ray changes appear.
Treatment
Activity modification is the main treatment. Reducing or modifying the aggravating lifts, particularly narrowing grip on the bench press and avoiding dips, often allows the bone to settle. This may take several months. Where symptoms persist despite a full period of modification, distal clavicle excision — removal of a small portion of the end of the collarbone — is effective and allows most lifters to return to training.

Warning Signs Of Acromioclavicular Joint Pain
There are a number of symptoms that could be warning signs of acromioclavicular joint injury and pain. It might start off as mild in the beginning but can get worse as the inflammation gets worse. Let’s look at some warning signs:
- You feel pain even while resting or during activity
- Your arm feels stiff when you raise the arm
- Stiffness when lifting your arm
- Playing sports requiring overhead actions becomes difficult
- You have a loss of strength and range of motion
- Night pain
- You are noticing tenderness and even swelling
What Are AC Joint Pain Symptoms?
The characteristic features
- Pain localized to the top of the shoulder, often at a point you can cover with a fingertip
- Pain reaching across the body — touching the opposite shoulder, fastening a seatbelt, washing under the opposite arm
- Pain with overhead activity, particularly at the top of the movement
- Pain lying on the affected side at night
- Tenderness to pressure directly over the joint
- Swelling over the joint
- A visible or palpable bump, after injury or in established arthritis
- Clicking, grinding, or popping with movement
Symptoms after an acute injury
- Sudden pain at the top of the shoulder after a fall
- Swelling and bruising
- A visible step or bump where the collarbone meets the shoulder, in higher-grade injuries
- Reluctance to move the arm
Where the pain usually stays
Acromioclavicular joint pain tends to stay on top of the shoulder, sometimes spreading slightly into the front of the shoulder or toward the base of the neck.
Dizziness is not a feature of AC joint problems. If you notice dizziness alongside shoulder or neck pain, have it assessed separately rather than assuming it comes from the AC joint, since it may have a different cause.
AC Joint Pain vs Other Shoulder Pain
Several shoulder conditions are easily confused, and the location of pain is the most useful starting point.
| Condition | Where pain is felt | Key features |
|---|---|---|
| AC joint problem | Top of the shoulder, pinpoint | Worse reaching across the body; tender to touch on the joint |
| Rotator cuff problem | Outer upper arm, often down toward the elbow | Worse lifting the arm out to the side; night pain common |
| Frozen shoulder | Deep, diffuse shoulder pain | Marked loss of movement in all directions, especially outward rotation |
| Glenohumeral arthritis | Deep in the shoulder, often felt at the back | Grinding, stiffness, loss of rotation |
| Referred neck pain | Top of the shoulder and down the arm | Pain changes with neck movement; tingling in the arm |
These can also coexist. AC joint bone spurs can crowd the space above the rotator cuff and contribute to rotator cuff irritation, so it is common to have both.
How AC Joint Pain Is Diagnosed
History and examination
The pattern is often recognizable from the history — pain on top of the shoulder, worse reaching across the body, often in someone who lifts or who has had a fall.
The examination looks for:
- Point tenderness directly over the AC joint
- Swelling, deformity, or a step at the joint
- Cross-body adduction test — the arm is brought across the chest toward the opposite shoulder. Pain on top of the shoulder suggests the AC joint, because this movement compresses it.
- Active compression test — the arm is held forward and turned so the thumb points down, then resisted. Pain on top of the shoulder points to the AC joint.
- Range of motion and rotator cuff strength, to identify or exclude coexisting problems
Imaging
X-ray is the first-line test. A specific angled view of the AC joint shows arthritis, bone spurs, osteolysis, and — after injury — how far the collarbone has displaced, which determines the grade. Comparing both shoulders on the same image helps assess displacement.
MRI shows the ligaments, cartilage disc, and bone swelling in detail. It is used for suspected osteolysis before X-ray changes appear, when the diagnosis is unclear, or before surgery.
Ultrasound can show joint swelling and fluid and is useful for guiding injections.
CT is occasionally used to assess complex injuries, particularly grade IV displacement.
An important caution: arthritic changes in the AC joint are extremely common on imaging in people with no shoulder pain at all. An X-ray showing AC joint arthritis does not by itself prove that the AC joint is the source of symptoms.
Diagnostic injection
This is the most reliable way to confirm the AC joint as the pain source. A small amount of local anesthetic is injected directly into the joint. If the pain is substantially relieved within minutes, the AC joint is confirmed as the source. The injection is often combined with a corticosteroid, making it both diagnostic and therapeutic. Ultrasound guidance improves accuracy, since the joint is small and easy to miss.

Conservative Treatment
Most AC joint pain — including arthritis, osteolysis, and lower-grade injuries — is treated without surgery, and most people improve.
Activity modification
The foundation. Avoiding or modifying the movements that load the joint allows it to settle:
- Lifting: narrow the grip on bench press, reduce the weight, and avoid dips and deep push-ups temporarily
- Overhead work: reduce the frequency or duration
- Sleeping: avoid lying on the affected side
- Reaching across the body: reduce where possible during a flare
Rest and a sling after injury
After an acute AC injury, a sling can be worn for comfort, typically for a short period of days to a couple of weeks depending on the grade. Prolonged sling use is not recommended, because it causes stiffness.
Ice and heat
Ice helps in the first days after an injury or during a flare. Apply it for around 15 to 20 minutes at a time, wrapped in a cloth, several times a day.
The current article advises that “the more the joint hurts, the more ice you should use” and suggests applying ice directly to the joint and massaging it with ice cubes. Applying ice directly to the skin risks cold injury, and increasing the amount in proportion to pain is not a sound principle. Always use a barrier, and keep to around 15 to 20 minutes.
Heat can help with stiffness in chronic arthritis once any acute flare has settled.
Medication
NSAIDs, oral or as a topical gel applied over the joint, reduce pain and inflammation. Topical gel is well suited to the AC joint because it sits just beneath the skin. Oral NSAIDs should be used at the lowest effective dose for the shortest period, and are not suitable for everyone.
Corticosteroid injection
An injection into the AC joint, ideally image-guided, can provide substantial relief for arthritis and persistent pain. It is also diagnostic, as described above. Relief often lasts weeks to months, and the number of injections into the same joint is usually limited.
Physical therapy
Physical therapy is an important part of recovery, particularly after injury and for chronic arthritis. A program typically covers:
- Restoring range of motion gradually after injury
- Strengthening the shoulder blade muscles, which control the scapula and reduce load on the AC joint
- Rotator cuff strengthening, which improves overall shoulder mechanics
- Posture work, since rounded shoulders increase AC joint load
- Graded return to lifting and sport
Joint and connective tissue support
Some people with AC joint osteoarthritis use supplements as part of a longer-term routine for joint comfort and mobility. It is worth being clear about their limits.
No supplement repairs cartilage, reverses AC joint arthritis, heals a ligament injury, or treats osteolysis. Supplements also do not replace the approaches that actually determine outcome here — activity modification, physical therapy, and, where needed, injection or surgery. And a supplement is not a response to an acute injury: a fall with a new bump or deformity on top of the shoulder needs assessment and grading.
Where the pain relates to established osteoarthritis of the AC joint, combination formulas such as Flexoplex Joint Support bring together ingredients commonly used to support joint comfort, flexibility, and everyday mobility, which may make it easier to keep up the strengthening and activity that conservative treatment depends on.
Practical points: speak with your doctor or pharmacist before starting any supplement, particularly if you take NSAIDs, blood thinners, or diabetes medication. Give any supplement a fair trial and assess honestly whether it is helping.
Surgical Options
Surgery is considered when conservative treatment has not worked after an adequate period — usually several months — or for high-grade injuries.
Distal clavicle excision
The main operation for AC joint arthritis and distal clavicle osteolysis.
A small portion of the outer end of the collarbone, typically less than a centimeter, is removed so the two bone ends no longer rub against each other. The space fills with scar tissue that acts as a cushion, and the stabilizing ligaments are preserved so the joint remains stable.
It can be performed:
- Arthroscopically — through small incisions using a camera, with generally faster early recovery
- Open — through a small incision directly over the joint
It is frequently combined with other shoulder procedures, such as smoothing bone spurs that are crowding the rotator cuff.
Outcomes are generally good, with most people experiencing substantial pain relief and returning to their usual activities, including lifting and sport. The current article cites a specific figure of 95 percent returning to pre-injury sport without a source; that figure should either be sourced or removed.
Ligament reconstruction
For high-grade AC separations — grades IV to VI, and selected grade III injuries — surgery restores the position of the collarbone and reconstructs the torn ligaments. Techniques include:
- Coracoclavicular ligament reconstruction, often using a tendon graft
- Suture button devices that hold the collarbone in place while the ligaments heal
- Hook plates, a metal plate that holds the collarbone down and is usually removed later
The choice depends on the injury, how long ago it happened, and the surgeon’s approach.
Risks
As with any surgery: infection, stiffness, persistent pain, and in reconstruction, loss of reduction where the collarbone gradually rides back up. Your surgeon will discuss the specific risks for your procedure.
Recovery and Returning to Activity
Recovery timelines vary considerably by the problem and treatment:
| Situation | Typical return to normal activity |
|---|---|
| Grade I sprain | A few weeks |
| Grade II injury | Several weeks |
| Grade III, treated non-surgically | Two to three months |
| Distal clavicle osteolysis, activity modification | Several months |
| Distal clavicle excision | Several weeks for daily activity; around three months for heavy lifting |
| Ligament reconstruction | Several months, with contact sport often later |
These are general ranges, and individual recovery depends on the severity, the treatment, and consistency with rehabilitation.
The current article states the joint can heal “sometimes in about two or three weeks.” That is reasonable for a mild grade I sprain but misleading as a general answer, since higher-grade injuries take considerably longer.
Returning to lifting
For lifters, return is usually gradual: starting with lighter weights, using a narrower bench press grip, and reintroducing dips and heavy pressing last. Returning to heavy pressing too early is a common cause of recurrence.
When to See a Doctor
Seek prompt assessment if you have:
- A fall onto the shoulder followed by a visible bump, step, or deformity
- Pain on top of the shoulder that persists beyond a few weeks
- Pain limiting sleep, work, or training
- Clicking or grinding with pain
- Weakness in the arm
Seek urgent same-day care if you have:
- A hot, red, swollen joint with fever, which can indicate infection
- Numbness, tingling, or coldness in the arm or hand after an injury
- A severe deformity after a high-energy injury
- Shoulder pain with chest pain, breathlessness, or sweating — left shoulder pain in particular can be a sign of a heart problem and needs emergency assessment
Frequently Asked Questions
Q: What does AC joint pain feel like?
Usually a localized ache on top of the shoulder that you can point to with one finger, worse when reaching across your body, lifting overhead, or lying on that side. It may feel tender to touch and can be accompanied by clicking.
Q: Is a separated shoulder the same as a dislocated shoulder?
No. A separated shoulder is an injury to the AC joint, where the collarbone and shoulder blade move apart on top of the shoulder. A dislocated shoulder is when the ball of the upper arm bone comes out of its socket. They are different injuries with different treatments.
Q: Can an AC joint injury heal on its own?
Lower-grade injuries, grades I and II, usually recover well without surgery. Grade III often does too. Higher-grade injuries, IV to VI, generally need surgery.
Q: Will the bump on my shoulder go away?
Often not. A bump after an AC separation is frequently permanent, even when the shoulder recovers fully and is pain-free. It is usually cosmetic rather than a sign of an ongoing problem.
Q: Can I still lift weights with AC joint pain?
Often yes, with modifications. Narrowing your bench press grip, reducing the weight, and avoiding dips and deep push-ups can let you keep training while the joint settles. Pressing through significant pain tends to prolong the problem.
Q: How long does AC joint arthritis last?
Arthritis itself does not reverse, but symptoms often settle with activity modification and physical therapy, and many people have long pain-free periods. Injection or surgery are effective options if symptoms persist.
Q: Is a cortisone injection in the AC joint painful?
The joint is small and close to the skin, so there is brief discomfort, but it is generally well tolerated. Image guidance improves accuracy, and many people feel relief from the local anesthetic almost immediately.
Q: What is the recovery time after AC joint surgery?
After distal clavicle excision, most people return to daily activities within a few weeks and to heavy lifting at around three months. Ligament reconstruction takes longer, often several months.
Q: Why does my shoulder hurt when I sleep on it?
Lying on the affected side compresses the AC joint directly. Sleeping on your back or the other side, with a pillow supporting the painful arm, often helps.
Q: What exercises help AC joint pain?
Strengthening the muscles that control the shoulder blade and the rotator cuff reduces load on the AC joint. A physical therapist can set an appropriate program. Exercises that load the joint heavily, such as dips and wide-grip pressing, are usually avoided until symptoms settle.
Conclusion
AC joint pain is common, and for most people it’s very manageable. Whether it comes from arthritis, a fall onto the shoulder, or years of heavy lifting, the large majority of cases improve without surgery.
The first step is identifying the source correctly. Pain you can point to on top of the shoulder, especially when reaching across your body, often comes from the AC joint. That’s a different problem from rotator cuff pain, and it responds to different treatment. A doctor can confirm the source with a simple examination, imaging, and sometimes a diagnostic injection.
From there, treatment usually starts with modifying the movements that aggravate the joint, along with ice, anti-inflammatory medication, and physical therapy to strengthen the muscles around the shoulder blade. For lifters, small changes such as narrowing the bench press grip often make a real difference. Where pain persists, a cortisone injection or a short surgical procedure to remove the end of the collarbone can provide lasting relief.
If you’ve had a fall and notice a new bump or step on top of your shoulder, or if your pain hasn’t settled after a few weeks, it’s worth getting it assessed. Most AC joint problems respond well to treatment, especially when they’re addressed early.
References
- https://www.ncbi.nlm.nih.gov/books/NBK493188/
- https://pmc.ncbi.nlm.nih.gov/articles/PMC8505126/
- https://pmc.ncbi.nlm.nih.gov/articles/PMC10638592/
- https://pmc.ncbi.nlm.nih.gov/articles/PMC7441096/