Overview Of Juvenile Arthritis
No one ever wants to see their kids in pain, but the sad fact is that many parents have to deal with this situation. It is because there is an estimated 294,000 children in the United States alone who suffer from juvenile arthritis.
Arthritis is usually viewed as an affliction of the elderly. Few people realize that the same type of affliction can be suffered in children. However, it’s important to note that juvenile arthritis is not quite the same as the kinds of arthritis that plague adults.
Rheumatoid arthritis in adults is no longer considered the same kind of affliction as juvenile arthritis. Though it was once thought that they were one in the same, new evidence has come to light, and the two are now separated.
If you have noticed that your child has been complaining about pains in the knees, ankles, wrists, fingers, or elbows, you should seek medical attention as soon as possible because JA is probably more common than you realize.
Explanation And Definition Of Juvenile Arthritis
The disease is known as Juvenile Arthritis is what’s known as auto-immune disease. An auto-immune disease is when the body attacks its own healthy and regenerative cells. In the case of JA, the body attacks the cells that protect the joints against inflammation and long-term damage.
The joints are where the bones meet, and inflammation in the joints can cause pain. Juvenile Arthritis could make it so that this inflammation becomes chronic, or it happens all the time over a long period.
Juvenile Arthritis is diagnosed in anyone under the age of 18 who is exhibiting this kind of chronic inflammation of the joints. First, the joint becomes inflamed, and then the joints stiffen, then there is some sort of joint damage. Finally, the growth of the joint is altered.
Juvenile Arthritis may last for up to 10 years after the initial diagnosis. There is a wide spectrum in terms of pain caused by JA. It may cause only mild pain or irritation, while severe cases can cause extreme pain. In other severe cases, JA can cause long-term damage to the joints.
The Different Types Of Juvenile Arthritis
Within the umbrella term of juvenile arthritis, there are more specific subsets of the disease. There are three main types of JA:
Juvenile idiopathic arthritis (JIA) is the umbrella term for chronic arthritis beginning before a child’s 16th birthday, lasting at least six weeks, with no other identifiable cause. “Idiopathic” means the cause is unknown.
JIA is not one disease. It is classified into subtypes based on how many joints are affected in the first six months and which other features are present. The subtype matters, because it shapes which complications to watch for and how the condition is treated.
Oligoarticular JIA
The most common subtype, accounting for roughly half of all cases.
- Affects four or fewer joints in the first six months
- Usually large joints, most often the knee, then the ankle
- Typically asymmetric — one knee rather than both
- Most common in young girls, often starting between ages two and four
- Carries the highest risk of uveitis, particularly in children with a positive ANA blood test
Many children with oligoarticular JIA do well. Some continue to have four or fewer joints involved, called persistent oligoarticular JIA. In others, more joints become involved after the first six months, called extended oligoarticular JIA, which behaves more like the polyarticular form.
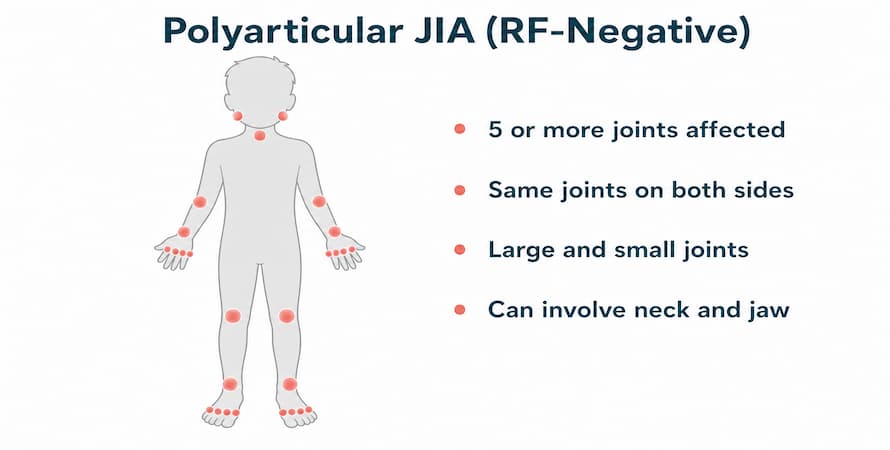
Polyarticular JIA, rheumatoid factor negative
- Affects five or more joints in the first six months
- Often both large and small joints, including the hands and feet
- Frequently symmetric
- Can involve the neck and the jaw joint
- Also carries a risk of uveitis
Polyarticular JIA, rheumatoid factor positive
- Also affects five or more joints, but with a positive rheumatoid factor blood test
- The subtype most similar to adult rheumatoid arthritis
- Usually begins in adolescence, more often in girls
- Symmetric small-joint involvement, particularly the hands
- Tends to be more persistent and more likely to cause joint damage without early treatment
Systemic JIA
One of the less common subtypes, around 10 percent of cases — not the most common, as the current article states.
Systemic JIA is different in kind from the other subtypes. It is now understood as largely an autoinflammatory condition, driven by the innate immune system rather than the adaptive immune system that underlies classic autoimmunity.
- Daily spiking fevers, often rising once or twice a day to 39°C (102°F) or higher and returning to normal in between
- A faint, salmon-pink rash that comes and goes, often appearing with the fever
- Arthritis, which may develop weeks or months after the fever begins
- Enlarged lymph nodes, liver, or spleen
- Inflammation of the lining around the heart or lungs
- Affects boys and girls equally, at any age in childhood
The serious complication to know about is macrophage activation syndrome (MAS), an uncontrolled immune overreaction that is a medical emergency. Warning signs include a persistent rather than spiking fever, a child becoming suddenly more unwell, bruising or bleeding, and confusion. It requires immediate hospital care.
Enthesitis-related arthritis
- Most common in older boys, typically from around age eight
- Affects the joints of the legs, the spine, and the sacroiliac joints
- Enthesitis — pain and swelling where tendons attach to bone, most characteristically at the heel
- Often associated with the gene marker HLA-B27
- Can cause acute uveitis, which, unlike the silent form, produces a painful red eye
- In some children it progresses toward ankylosing spondylitis in adulthood
Juvenile psoriatic arthritis
- Arthritis together with psoriasis, or with features suggesting it — nail pitting, dactylitis, or psoriasis in a close relative
- Dactylitis, where a whole finger or toe swells, giving a sausage-like appearance
- Often asymmetric
- The arthritis sometimes appears years before the skin condition
- Carries a risk of uveitis
Undifferentiated arthritis
Arthritis that fits none of the categories above, or fits more than one. This is a genuine classification rather than a failure to diagnose.
Comparing the Subtypes
| Subtype | Share of cases | Joints affected | Typical age | Key feature | Uveitis risk |
|---|---|---|---|---|---|
| Oligoarticular | ~50% | 4 or fewer, often knee | 2–4, mostly girls | Asymmetric large joints | Highest — often silent |
| Polyarticular RF-negative | ~20% | 5 or more | Any age | Symmetric, large and small | Moderate |
| Polyarticular RF-positive | ~5% | 5 or more | Adolescence, mostly girls | Resembles adult RA | Low |
| Systemic | ~10% | Variable | Any age | Daily spiking fever and rash | Low |
| Enthesitis-related | ~10% | Legs, spine | 8+, mostly boys | Heel and tendon pain | Moderate — often painful |
| Psoriatic | ~5% | Variable, asymmetric | Two peaks | Sausage digits, nail changes | Moderate |
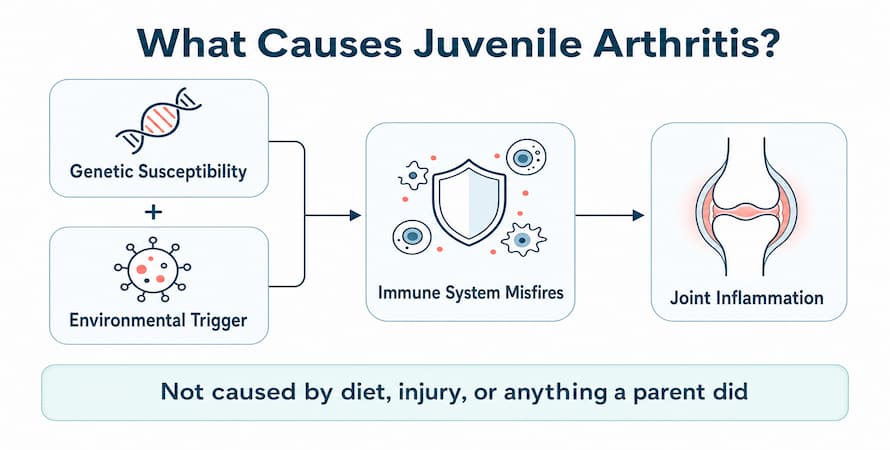

What Causes Juvenile Arthritis?
The cause is not fully understood, but current evidence points to a combination of genetic susceptibility and an environmental trigger.
- Genetics play a role. The current article states that heredity “has been dismissed” as a cause. That is not accurate. Specific genetic markers, particularly within the HLA system, are clearly associated with several JIA subtypes, and HLA-B27 is strongly linked to enthesitis-related arthritis. The article itself notes genetic factors for systemic and psoriatic JIA two sections earlier.
- What is true is that JIA is not inherited in a simple, predictable way. Having a sibling with JIA only modestly increases a child’s risk, and most children with JIA have no affected relative.
- An environmental trigger is thought to set the process off in a genetically susceptible child. Infections are the most studied candidates, though no single trigger has been confirmed.
- What does not cause JIA: nothing a parent did or did not do. It is not caused by diet, injury, cold weather, or anything in the child’s upbringing. This is worth stating plainly, because parents frequently wonder.
Read More: Everything You Need to Know About Psoriatic Arthritis
Symptoms
Joint symptoms
- Swelling in one or more joints, often without redness
- Morning stiffness or stiffness after naps, often the most noticeable symptom
- Limping, particularly first thing in the morning, which improves as the day goes on
- Reluctance to use a joint — a young child may stop using an arm or want to be carried
A point that often confuses parents
Young children frequently do not complain of pain. A toddler with an inflamed knee may simply stop walking, walk differently, or refuse activities they enjoyed, without saying anything hurts. Morning limping that settles by midday is a common early sign that is easy to put down to tiredness or a knock. Changes in how a child moves are often more informative than whether they report pain.
Systemic symptoms
Particularly in systemic JIA:
- Daily spiking fevers
- A pale pink rash that comes and goes
- Tiredness and loss of appetite
- Enlarged lymph nodes
Eye symptoms
Uveitis may cause red, painful, or light-sensitive eyes, or blurred vision — but in oligoarticular and polyarticular JIA it usually causes no symptoms at all, which is why screening matters. See the next section.
Growth-related signs
- One leg growing longer than the other, due to inflammation near the growth plate of an affected knee
- A small or receding jaw, if the jaw joint is involved
- Slowed overall growth
Eye Inflammation: The Complication Parents Must Know About
Uveitis is inflammation inside the eye. In oligoarticular and polyarticular JIA it usually develops without any symptoms — no redness, no pain, no complaint from the child. By the time vision is affected, damage may already be permanent. Untreated, it can lead to cataracts, glaucoma, and loss of vision.
It is also independent of the joints. A child’s eyes can be inflamed even when their arthritis is well controlled or in remission.
What this means in practice
- Every child with JIA needs regular eye screening by an ophthalmologist, using a slit-lamp examination. A standard eye test or school vision check does not detect it.
- How often depends on the subtype, the child’s age, their ANA result, and how long they have had JIA. Children at the highest risk may be screened every three months.
- Screening continues even when the arthritis is quiet.
Parents should ask the rheumatologist which screening schedule applies to their child, and keep every appointment even when their child’s eyes seem completely normal.
How JIA Is Diagnosed
There is no single test that confirms JIA. It is diagnosed by a pediatric rheumatologist based on the pattern of symptoms, examination findings, and tests that exclude other causes.
The criteria
- Arthritis beginning before age 16 — not under 18, as the current article states
- Lasting at least six weeks
- No other identifiable cause
Tests used
| Test | Why it is done |
|---|---|
| ANA (antinuclear antibody) | Does not diagnose JIA, but a positive result raises uveitis risk and changes eye screening frequency |
| Rheumatoid factor and anti-CCP | Identify the RF-positive polyarticular subtype |
| HLA-B27 | Supports enthesitis-related arthritis |
| ESR and CRP | Measure inflammation, often very high in systemic JIA |
| Full blood count | Checks for anemia and helps exclude other conditions |
| Ultrasound or MRI | Detect joint inflammation and fluid |
| X-ray | Identifies joint damage or excludes fracture |
| Joint fluid analysis | Excludes infection when a single joint is swollen |
Conditions that must be excluded
This is a significant part of diagnosis, because several serious conditions can look like JIA:
- Septic arthritis — a bacterial joint infection, which is an emergency
- Reactive arthritis — following an infection elsewhere
- Lyme disease — in endemic areas
- Leukemia — which can present with joint and bone pain. Red flags include pain out of proportion to what the joint looks like, night pain, bone pain, and abnormal blood counts
- Injury
- Other autoimmune conditions, such as lupus
Because some of these are serious, a child with persistent joint swelling or an unexplained limp should be assessed rather than monitored at home.
Treatment
The goal
Modern JIA treatment aims for inactive disease or remission — no active joint inflammation — rather than simply symptom relief. This is achievable for many children, and it is what prevents permanent joint damage and growth problems.
Medication
NSAIDs such as ibuprofen or naproxen relieve pain and inflammation. They are usually a starting point or an addition, not a treatment on their own for most children.
Joint injections of a long-acting corticosteroid are widely used, particularly in oligoarticular JIA. A single injection into a swollen knee can settle it for months.
Methotrexate is the most widely used disease-modifying medication in JIA. It acts on the underlying immune process and requires regular blood monitoring.
Biologic medications target specific parts of the immune system. They are used when methotrexate is insufficient, and have transformed outcomes, particularly for polyarticular and systemic JIA. Systemic JIA is often treated with biologics that block specific inflammatory signals.
Oral corticosteroids are used sparingly and short-term, particularly in systemic JIA, because long-term use affects growth and bone health in children.
All treatment decisions are made by a pediatric rheumatologist and monitored closely.
Physical and occupational therapy
- Physical therapy maintains range of motion, strength, and function, and is part of treatment rather than an optional extra
- Occupational therapy helps with daily tasks, handwriting, and school activities
- Splints, sometimes worn at night, help prevent joint contractures
Surgery
Rare today, largely because of effective medication. It may be needed for established joint damage, leg length differences, or jaw problems.

Long-Term Management
JIA is managed over years, and much of that management happens at home and at school rather than in clinic.
Staying active
Physical activity is encouraged for children with JIA, not restricted. Exercise maintains muscle strength around the joints, protects bone health, and supports mood and sleep. Swimming and cycling are often well tolerated. During a flare, activity may need scaling back, but long-term inactivity worsens stiffness and weakness.
Most children with well-controlled JIA can take part in sport, though some activities may need discussion with the care team.
Nutrition
There is no special diet that treats JIA. A balanced diet supports growth and general health, which matters in a condition that can affect growth.
Calcium and vitamin D deserve particular attention. Children with JIA can be at risk of lower bone density, especially if they have taken corticosteroids. The rheumatology team may check vitamin D levels and advise on intake or supplementation.
Omega-3 fatty acids from oily fish are part of a healthy diet. The evidence that they reduce JIA activity is limited, and they are not a substitute for prescribed treatment.
Complementary approaches
Some families explore complementary approaches alongside medical care. A few principles keep this safe:
- Discuss everything with the rheumatology team first. This applies to supplements, herbal products, and vitamins, because some interact with methotrexate and biologics, and doses suitable for adults are not suitable for children.
- Adult products are not designed for children. Supplements marketed for adult joint health are not formulated or tested for pediatric use.
- Nothing complementary replaces disease-modifying treatment. The main risk of complementary approaches in JIA is not usually the approach itself — it is delay in effective treatment while it is tried.
- Comfort measures genuinely help day to day. Warm baths in the morning ease stiffness, and heat pads or cold packs can help a sore joint.
- Evidence for acupressure and acupuncture in children with JIA is limited.
Sleep
Pain and inflammation disrupt sleep, and poor sleep worsens pain and fatigue. A consistent bedtime routine and a warm bath before bed can help, and persistent sleep problems are worth raising with the care team.
Emotional wellbeing
Living with a chronic condition affects a child’s mood, confidence, and friendships, and it affects the whole family. Anxiety and low mood are more common in children with JIA. Psychological support, peer groups, and family support organizations are valuable parts of care rather than a sign that things are going badly.
Growing Up With JIA
School
Many children need some adjustments: extra time to move between classes, a second set of textbooks to avoid heavy bags, rest breaks, adapted physical education, and flexibility around medical appointments. In the US, a formal 504 plan can secure these. A letter from the rheumatology team helps.
Transition to adult care
As children reach their late teens, their care moves from pediatric to adult rheumatology. Good transition programs prepare young people to manage their own appointments, medications, and decisions. It is a common point for people to drop out of care, which is worth guarding against.
Long-term outlook
Outcomes have improved dramatically with modern treatment. Many children achieve remission, and a large proportion reach adulthood with little or no joint damage. Some continue to have active arthritis as adults. Outlook depends heavily on the subtype and on how early effective treatment began.
When to Seek Medical Care
See a doctor promptly if your child has:
- A swollen joint lasting more than a few days without a clear injury
- A limp, especially in the morning, that persists
- Joint stiffness that is worse after sleep or rest
- A child who stops using an arm or leg, or who stops walking
- Joint symptoms together with a fever lasting more than a few days
Seek urgent same-day care if your child has:
- A single hot, red, very painful joint with fever — possible septic arthritis
- A daily spiking fever with a rash
- A painful red eye, sensitivity to light, or any change in vision
- Joint or bone pain that wakes them at night, or pain far worse than the joint looks
If your child has systemic JIA, seek emergency care for a persistent fever that stops spiking, sudden deterioration, bruising or bleeding, or confusion, which can signal macrophage activation syndrome.
Frequently Asked Questions
Q: Does juvenile arthritis go away?
It can. Many children achieve remission, particularly with oligoarticular JIA and with early treatment. Some continue to have active arthritis into adulthood. It is not possible to predict with certainty at diagnosis, and remission does not mean eye screening can stop.
Q: Does juvenile arthritis shorten life expectancy?
For the great majority of children, no. The current answer — that it “may shorten life expectancy” — is alarming and not an accurate picture of modern outcomes. Systemic JIA carries a small risk of serious complications such as macrophage activation syndrome, which is why prompt treatment and monitoring matter.
Q: Is juvenile arthritis the same as adult rheumatoid arthritis?
No. Only the RF-positive polyarticular subtype closely resembles adult rheumatoid arthritis. The other subtypes are distinct conditions with different features, complications, and outlooks.
Q: Is JIA hereditary?
Genetics contribute, but not in a simple way. Having an affected sibling modestly increases risk, but most children with JIA have no affected relative, and most siblings of children with JIA never develop it.
Q: Can my child still play sports?
Usually yes, and physical activity is encouraged. During flares, activity may need adjusting. Discuss specific sports with the care team, particularly if the neck or jaw is involved.
Q: Why does my child need eye checks if their eyes seem fine?
Because uveitis in JIA usually causes no symptoms until damage has occurred. Regular slit-lamp examination by an ophthalmologist is the only way to catch it early, and it continues even when the arthritis is under control.
Q: Is methotrexate safe for children?
At the doses used for JIA, methotrexate has a long track record and is generally well tolerated, with regular blood tests to monitor for side effects. It is used at much lower doses than in cancer treatment.
Q: What are the first signs of JIA?
Often a limp that is worse in the morning, a swollen joint without an injury, stiffness after sleep, or a young child who stops using a limb. Young children frequently do not complain of pain, so changes in how they move matter more.
Q: Can diet cure juvenile arthritis?
No. There is no diet that treats JIA. A balanced diet with adequate calcium and vitamin D supports growth and bone health, which is valuable, but it does not replace medical treatment.
Conclusion
JA can have a severe impact on your child’s life. That’s why it’s always important to know the juvenile arthritis causes, symptoms and how it may be treated. It’s also important to listen to your child in order to catch the early warning signs of juvenile arthritis.
References
https://pmc.ncbi.nlm.nih.gov/articles/PMC12439517/
https://pmc.ncbi.nlm.nih.gov/articles/PMC10527260/
https://pmc.ncbi.nlm.nih.gov/articles/PMC12869327/
https://www.mayo.edu/research/clinical-trials/diseases-conditions/uveitis