Introduction
The muscle is an important but often overlooked muscle of the upper back and shoulder region. Located beneath the shoulder joint, this muscle plays a key role in controlling arm movement, stability, and strength during daily activities and athletic performance. Although it is not part of the rotator cuff, the teres major works closely with surrounding shoulder and back muscles, making it essential for coordinated upper-body motion.
Many people search for information about the teres major due to shoulder pain, upper-back tightness, or discomfort during lifting and pulling movements. Athletes, weightlifters, swimmers, climbers, and individuals with poor posture often experience strain or overuse of this muscle without realizing its involvement. In some cases, teres major pain may be mistaken for rotator cuff or latissimus dorsi issues.
This article provides a comprehensive overview, including its anatomy, function, and relationship to nearby muscles. It also explores common causes of this muscle’s pain, typical symptoms, diagnostic approaches, treatment options, targeted exercises, and prevention strategies. Understanding how this muscle works can help manage discomfort, improve shoulder health, and reduce the risk of future injury.
Anatomy of the Teres Major Muscle
This muscle is located in the upper back, extending from the lower portion of the shoulder blade to the upper arm bone. It lies inferior to the teres minor and works closely with the latissimus dorsi, forming part of the posterior axillary fold. Although small compared to larger back muscles, it plays a significant functional role.
Anatomically, this originates from the posterior surface of the inferior angle of the scapula (shoulder blade). From there, it travels upward and laterally to insert onto the medial lip of the intertubercular sulcus of the humerus. This insertion allows the muscle to influence shoulder movement directly.
This muscle receives its blood supply primarily from branches of the circumflex scapular artery, ensuring adequate circulation during activity. It is innervated by the lower subscapular nerve, which originates from the posterior cord of the brachial plexus. Proper nerve function is essential for coordinated contraction and strength.
A common point of confusion is the difference between the teres major and teres minor. While they are adjacent, the teres major is larger, stronger, and not considered part of the rotator cuff. In contrast, it contributes to shoulder stabilization. Understanding this distinction is important when assessing shoulder pain or dysfunction.
Function of the Teres Major Muscle
The muscle is primarily responsible for three key shoulder movements: adduction, extension, and internal rotation of the arm. These actions are essential for pulling movements and bringing the arm downward or inward toward the body.
During activities such as rowing, climbing, swimming, or performing pull-ups, the teres major works synergistically with the latissimus dorsi to generate power and control. It also assists in movements like reaching down, lifting objects, and stabilizing the arm during forceful actions.
Although it is not a stabilizer of the shoulder joint in the same way as the rotator cuff, it contributes indirectly to joint stability by supporting controlled movement patterns. Proper activation helps prevent excessive strain on surrounding muscles and connective tissues.
In everyday activities, it plays a role in tasks such as carrying groceries, pushing doors, or lowering the arm from an overhead position. When functioning properly, it allows smooth, pain-free motion. Dysfunction or weakness in this muscle can alter movement patterns, increasing the risk of shoulder strain or compensatory injuries.
Teres Major vs Teres Minor: Key Differences
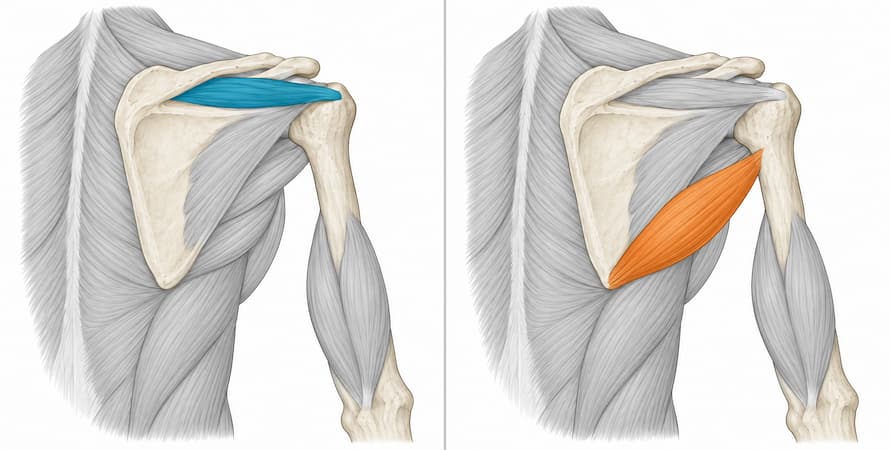
Although they share similar names and locations, the teres major and teres minor are distinct muscles with different roles. Structurally, the teres major is larger and thicker, while the teres minor is smaller and more delicate.
Functionally, the teres minor is part of the rotator cuff and plays a crucial role in stabilizing the shoulder joint and externally rotating the arm. On the other hand, focuses on generating movement rather than stabilization, particularly internal rotation and extension.
Due to their proximity, pain originating from the teres major is often misdiagnosed as rotator cuff pathology. This overlap can complicate diagnosis and delay appropriate treatment if not properly assessed.
Clinically, distinguishing between teres major and teres minor involvement is important for targeted rehabilitation. Treating a movement-based muscle like the teres major requires a different approach than treating stabilizing rotator cuff muscles.
Common Causes of Teres Major Pain or Injury
Teres major pain rarely arrives out of nowhere. In most cases it follows a pattern of repeated loading, a sudden overload, or a postural habit that keeps the muscle shortened for hours at a time.
Overhead throwing and racket sports
Baseball pitchers, javelin throwers, tennis players, and volleyball hitters place enormous demand on the teres major during the deceleration phase — the moment after release when the arm has to slow down. This eccentric loading is where most throwing-related strains occur.
Pull-ups, lat pulldowns, and rowing
Any exercise that drives the elbow down and back recruits the teres major heavily. Problems tend to appear when volume climbs quickly, when the movement is performed with a shrugged shoulder, or when someone drops into a dead hang from a fully stretched position without control.
Swimming
The freestyle and butterfly pull both combine adduction, extension, and medial rotation — the teres major’s exact job description. High-yardage swimmers frequently develop tightness here long before it becomes painful.
Sudden reaching or catching
A fast, unplanned movement — catching something heavy as it falls, grabbing a handrail to stop a stumble, breaking a fall with an outstretched arm — can overload the muscle in a single instant.
Sleeping position
Sleeping with the arm overhead or tucked underneath the body holds the teres major in a shortened or stretched position for hours. Many people first notice this pain on waking and assume they “slept on it wrong,” which in a sense is accurate.
Desk posture and rounded shoulders
Prolonged sitting with the shoulders rolled forward keeps the teres major in a shortened position. Over weeks and months, it adapts to that length. The pain often shows up not at the desk but during the first overhead reach afterward.
Compensating for a weak rotator cuff
When the rotator cuff is not doing its share of the work, larger muscles take over. The teres major is one of the muscles that picks up the slack, and it eventually protests. This is why treating teres major pain in isolation often fails — the underlying cause may sit elsewhere in the shoulder.

Symptoms of Teres Major Strain or Dysfunction
The single most useful thing to understand about this muscle is that the pain is usually not felt where the muscle is.
Where the pain shows up
- A deep ache at the back of the shoulder, roughly over the rear deltoid.
- Pain or tightness in the armpit region, particularly on reaching overhead.
- A band of discomfort tracking down the back of the upper arm, over the triceps.
- Occasional referral as far as the back of the forearm, which leads some people to suspect a nerve problem.
Because the referral pattern sits over the posterior deltoid, teres major problems are commonly misattributed to the rotator cuff, bursitis, or impingement.
Related: Your Guide to the Best Deltoid Exercises
Movement-related signs
- Pain or restriction when raising the arm overhead, especially in the last part of the range.
- Difficulty reaching behind the back.
- A pulling sensation during pull-ups, pulldowns, or swimming.
- Reduced ability to fully straighten the arm overhead compared with the other side.
- Discomfort that eases with movement and returns after rest, which is typical of muscular tightness rather than joint pathology.
Signs that point to a more significant injury
- A sudden sharp pain or a tearing sensation during a throw or a heavy pull.
- Immediate loss of strength in the arm.
- Bruising appearing in the armpit or along the inner upper arm within a day or two.
- A visible gap, lump, or change in contour near the armpit.
Any of these warrant assessment rather than self-management.
Teres Major Trigger Points and Self-Release
A trigger point is a hypersensitive band within a tight muscle that produces pain both locally and in a predictable pattern elsewhere. The teres major is a common site, and its trigger points are among the most frequently missed in the shoulder.
The referral pattern
Teres major trigger points typically refer pain to the back of the shoulder over the posterior deltoid, and sometimes further down over the long head of the triceps. Someone with an active trigger point here will often point to the rear of the shoulder and say the pain feels like it is “inside the joint,” even though the source is several inches away.
How to locate it
- Lie on your side with the painful shoulder facing up, or stand and reach across your chest.
- Find the outer border of the shoulder blade and follow it down toward the bottom tip.
- Just above that lower corner, pinch the fold of muscle between your thumb and fingers — you will be holding the teres major and part of the latissimus dorsi together.
- A trigger point feels like a firm nodule or taut band, and pressing it usually reproduces the familiar back-of-shoulder ache.
Self-release with a ball
- Place a lacrosse ball, tennis ball, or massage ball against a wall.
- Position the ball just below your armpit, against the outer edge of the shoulder blade.
- Lean into the wall with enough pressure to feel a strong but tolerable sensation — around 6 out of 10, never sharp.
- Hold still for 30 to 60 seconds, breathing normally, until the sensation begins to soften.
- Slowly raise and lower the arm a few times while maintaining pressure to add a movement component.
- Repeat on two or three tender spots along the muscle.
This can be done lying on the floor instead of against a wall for more pressure, though the wall version is easier to control.
Foam roller variation
Lie on your side with a foam roller positioned under the armpit and the arm extended overhead. Roll slowly through a short range, pausing on tender areas. Keep the movement small — long, fast rolling passes tend to skip over the spots that matter.
Practical cautions
- Avoid pressing directly into the armpit itself, where nerves and blood vessels are relatively superficial.
- Stop if you feel tingling, numbness, or radiating electrical sensation.
- Do not work an area that is bruised, acutely swollen, or painful at rest.
- Self-release is best used alongside stretching and strengthening rather than on its own.

Diagnosing Teres Major Problems
Diagnosis is primarily clinical. A physician or physical therapist will usually work through the following.
History
When the pain started, what you were doing at the time, whether there was a specific moment of injury, what makes it better or worse, and your training or occupational loading pattern.
Observation and palpation
Comparing both sides for contour and symmetry, then palpating along the outer scapular border and the fold of the posterior axilla to reproduce symptoms.
Range of motion testing
Overhead flexion and external rotation are the movements most often limited by a tight teres major. A restricted overhead reach that improves after soft tissue work points toward muscular restriction rather than joint pathology.
Resisted strength testing
Resisted adduction, extension, and medial rotation with the arm at the side. Pain on resisted testing suggests the muscle or its tendon is involved; weakness without pain suggests something more significant.
Ruling out other causes
Because the referral pattern overlaps so heavily with other shoulder conditions, a thorough assessment will also screen for rotator cuff tendinopathy, subacromial impingement, cervical spine referral, and quadrangular space syndrome.
Teres Major Strain vs Tear: Grades and Healing Time
Strain and tear describe the same type of injury at different severities. Clinicians usually grade muscle injuries on a three-point scale.
| Grade | What has happened | Typical symptoms | General recovery window |
|---|---|---|---|
| Grade 1 (mild) | Overstretching with microscopic fiber damage | Mild ache, minimal strength loss, full or near-full range of motion | Around 1 to 3 weeks |
| Grade 2 (moderate) | Partial tear of the muscle or tendon | Noticeable pain, weakness, possible bruising, restricted overhead reach | Around 4 to 8 weeks |
| Grade 3 (severe) | Complete tear or avulsion from the bone | Sudden intense pain, marked weakness, bruising, possible visible deformity | Several months; occasionally surgical |
These ranges are general. Actual recovery depends on age, training history, the demands of your sport or job, and how consistently rehabilitation is followed.
When imaging is warranted
Most mild strains do not require imaging. An MRI or ultrasound is usually considered when:
- Weakness persists beyond two to three weeks despite rest.
- There was an audible pop or a tearing sensation at the time of injury.
- Significant bruising or a palpable defect is present.
- The injury occurred in a throwing athlete, where teres major and latissimus dorsi injuries are well documented and return-to-play timing matters.
Returning to activity
A reasonable progression is pain-free range of motion first, then light isometric work, then loaded strengthening, then sport-specific movement. Returning to throwing or heavy pulling before full pain-free strength has been restored is the most common reason these injuries recur.
Related: 9 Effective Upper and Lower Back Exercises for Better Posture
Treatment Options
Most teres major problems respond to conservative care.
Early management
In the first few days after an acute strain, relative rest is appropriate — avoid the movements that provoke symptoms, but keep the shoulder moving gently within a comfortable range. Complete immobilization tends to slow recovery. Ice may be used for short periods in the first 48 hours if it helps with comfort.
Manual therapy and soft tissue work
Massage, myofascial release, dry needling, and instrument-assisted soft tissue work are all used clinically for this muscle. Response varies between individuals, and these approaches generally work best when paired with an exercise program rather than used alone.
Heat
Once the acute phase has passed, heat before stretching can make the tissue more comfortable to work with.
Over-the-counter pain relief
Non-steroidal anti-inflammatory medications are sometimes used short term. These carry their own considerations, and anyone with stomach, kidney, cardiovascular, or bleeding concerns should check with a pharmacist or physician before using them.
Physical therapy
A structured program addressing both the teres major and the wider shoulder complex — including scapular control and rotator cuff capacity — offers the most durable outcome, particularly where the strain was a symptom of compensation rather than a one-off overload.
Nutrition and joint support
General measures that support musculoskeletal health — adequate protein, sufficient vitamin D, and staying hydrated — play a supporting role in tissue recovery. Some people also use joint health supplements as part of a broader routine; these are best viewed as one element alongside rehabilitation rather than a replacement for it.

Exercises for Strengthening and Stretching the Teres Major
Strengthening comes after pain has settled and range of motion has been restored. The goal is not to isolate the teres major — that is neither practical nor desirable — but to build capacity across the movements it contributes to.
General guidance: start with 2 to 3 sets of 10 to 15 repetitions using light resistance, and progress gradually. Stop any exercise that reproduces sharp pain.
1. Straight-arm pulldown
Using a cable or resistance band anchored overhead, keep the arms relatively straight with a soft elbow bend and pull the bar down toward the thighs. Keeping the arms straight emphasizes the teres major and lat over the biceps.
2. Single-arm dumbbell row
Support yourself on a bench and row the dumbbell toward the hip rather than the chest. Driving the elbow back and down recruits the teres major more directly than a high row.
3. Lat pulldown with controlled eccentric
Perform the pulldown normally, then take three to four seconds on the way up. The controlled lengthening phase is where the muscle builds resilience.
4. Resistance band internal rotation
Anchor a band at elbow height, stand side-on, tuck the elbow to your side at 90 degrees, and rotate the forearm across the body. This trains the medial rotation component in a low-load position.
5. Prone Y-T-W raises
Lying face down, lift the arms in a Y, then a T, then a W shape. These build the scapular stabilizers that reduce compensatory loading on the teres major.
6. Pull-up or assisted pull-up
Once strength allows, pull-ups load the muscle through a full range. Use a band or an assisted machine to begin, and avoid dropping into an uncontrolled dead hang.
7. Dumbbell pullover
Lying across a bench, lower a single dumbbell behind the head with a soft elbow bend, then draw it back over the chest. Take care with the range — go only as far as your shoulder mobility comfortably allows.
8. Isometric hold
Press the elbow down and back into a wall or against your own hand, hold 10 to 15 seconds, and repeat. Isometrics are well tolerated early in rehabilitation when loaded movement is still uncomfortable.

How to Stretch the Teres Major
Stretching addresses the shortened position the muscle adopts with desk posture, swimming, and repetitive pulling. Work within a comfortable range — a stretch should feel like a pull, never a pinch or a sharp pain.
General guidance: hold each stretch 30 seconds, repeat 2 to 3 times per side, and aim for once or twice daily. Breathe normally throughout.
1. Overhead side-bend stretch
Stand tall and raise the arm on the tight side overhead. Grasp that wrist with the opposite hand and gently lean away, bending sideways at the waist. You should feel the stretch along the outer edge of the shoulder blade and into the armpit.
2. Doorway lat and teres stretch
Stand in a doorway and grip the frame overhead with one hand. Step forward with the same-side foot and allow your body weight to carry you gently through, keeping the arm straight. Rotate the torso slightly away from the stretching arm to increase the effect.
3. Child’s pose with side reach
From a kneeling position, sit back onto your heels and walk both hands forward. Then walk the hands over to one side, keeping the hips centered. Hold, and feel the stretch down the side of the back and into the armpit.
4. Cross-body reach
Bring the arm across the chest at roughly shoulder height and use the opposite hand to draw it further across. This targets the posterior shoulder broadly, including the teres major.
5. Wall-supported overhead reach
Stand facing a wall about a forearm’s distance away. Place both forearms on the wall and slide them upward while keeping the ribs down and the lower back flat. Stop where you feel tension and hold.
6. Sleeper stretch variation
Lie on the affected side with the shoulder and elbow bent at 90 degrees. Use the top hand to gently rotate the forearm toward the floor. This one targets medial rotation restriction and should be performed very gently.
Prevention Tips
- Warm up the shoulder before overhead activity. Arm circles, band pull-aparts, and light rotation work prepare the tissue for load.
- Increase training volume gradually. Sudden jumps in pull-up volume, swim yardage, or throwing count are the most common trigger.
- Balance pulling with pushing. A program heavy in pulldowns and rows without corresponding pressing and external rotation work encourages the muscle to shorten.
- Train the rotator cuff. Building cuff capacity reduces the compensatory load that falls on the teres major.
- Address desk posture. Regular breaks, a screen at eye height, and periodic overhead reaching break up long periods of shortened positioning.
- Watch your sleeping position. If you consistently wake with back-of-shoulder pain, try a pillow under the upper arm to stop it drifting overhead.
- Stretch consistently rather than intensely. Short daily stretching outperforms occasional aggressive sessions.
When to See a Doctor or Physical Therapist
Medical evaluation is recommended if teres major pain persists despite rest or worsens over time. Loss of strength, numbness, or pain interfering with daily activities warrants professional attention.
Early assessment can prevent chronic dysfunction and ensure appropriate care.
Frequently Asked Questions
Q. What is the Teres Major muscle?
This is a muscle located in the upper back that connects the shoulder blade to the upper arm. It helps control arm movement, particularly pulling, lifting, and internal rotation of the shoulder.
Q. Where is the Teres Major located?
This muscle is located on the lower part of the scapula (shoulder blade) and runs to the upper humerus. It sits just below the teres minor and works closely with the latissimus dorsi.
Q. What does the Teres Major muscle do?
The teres major assists with shoulder adduction, extension, and internal rotation. It plays an important role in activities such as rowing, climbing, swimming, and lifting objects.
Q. Is the Teres Major part of the rotator cuff?
No, the teres major is not part of the rotator cuff. Although it is near the rotator cuff muscles, it primarily supports movement rather than joint stabilization.
Q. What causes Teres Major pain?
Overuse, poor posture, repetitive pulling motions, improper lifting techniques, or muscle imbalances often cause teres major pain. Athletes and desk workers commonly experience strain in this muscle.
Q. How does the pain feel?
Pain from the teres major is typically felt in the back of the shoulder or upper arm and may radiate toward the armpit. It can worsen with pulling movements or when lowering the arm.
Q. Can the Teres Major pain be mistaken for a rotator cuff injury?
Yes, this pain is often confused with rotator cuff problems due to its location. A proper physical examination helps distinguish between the two.
Q. How is a Teres Major injury diagnosed?
Diagnosis usually involves a physical exam, movement testing, and evaluation of posture and strength. Imaging, such as MRI or ultrasound, may be used if symptoms persist.
Q. How is the pain treated?
Treatment may include rest, activity modification, physical therapy, stretching, strengthening exercises, and posture correction. Most cases improve with conservative care.
Q. Can exercises help strengthen the Teres Major?
Yes, exercises such as rows, lat pulldowns, resistance band work, and targeted stretches can help strengthen and support the teres major when performed correctly.
Q. How long does it take for a Teres Major strain to heal?
Recovery time varies depending on severity, but mild strains may improve within a few weeks, while more significant injuries may take several months with proper rehabilitation.
Q. When should I see a healthcare professional?
You should seek professional evaluation if pain persists, worsens, or is accompanied by weakness, numbness, or difficulty performing daily activities.
Final Thoughts
The muscle plays a vital role in shoulder movement and upper-body strength. Understanding its anatomy, function, and injury patterns allows for better prevention and management of pain.
Early care, proper movement mechanics, and balanced training are key to maintaining teres major health. With the right approach, most individuals can restore function and prevent recurring issues, supporting long-term shoulder performance and comfort.
References
https://pmc.ncbi.nlm.nih.gov/articles/PMC2696782/